

Do you need to schedule an appointment?
Outer Hip Pain Keeping You From Running, Walking, or Sleeping Comfortably?
Does This Sound Familiar?
If you experience a deep, aching pain on the outside of your hip that worsens when walking, climbing stairs, running, or lying in bed at night, you’re not alone.
At Performance Sport & Spine, we help you understand your hip pain, manage irritation, and progressively rebuild your strength so you can return to the activities you love.
1. What Is Gluteal Tendinopathy?
Gluteal tendinopathy affects the gluteus medius and minimus tendons on the outside of your hip. These muscles help stabilize your pelvis during walking, running, and other single-leg activities.
When the tendons struggle to tolerate everyday loads, movement can become painful.
Outer hip pain was once commonly called “trochanteric bursitis.” Today, we know gluteal tendinopathy is a common contributor to greater trochanteric pain syndrome (GTPS), although other tissues may also be involved.
Struggling with persistent outer hip pain?
Performance Sport & Spine can help you understand your symptoms and find a path toward recovery.
 2. Common Symptoms
- Outer hip pain: A deep ache on the outside of the hip, can radiate into the buttocks or down the leg, rarely past the knee.
- Night pain: Discomfort when lying on the affected hip or when your upper leg falls across your body.
- Morning stiffness: Aching when getting out of bed or standing after sitting.
- Activity-related pain: Symptoms during walking, running, climbing stairs, or prolonged standing.
- Sensitivity to pressure: Discomfort when crossing your legs or leaning heavily onto one hip.
Other conditions, including hip joint and lumbar spine problems, can cause similar symptoms. An assessment helps identify the likely source of your pain.

Patient Success Stories
“I suffered from what I now know to be gluteal tendinopathy for over a year. I had been to 3 different physical therapists without positive results and felt like I was at the end of my rope. Dr. Zach’s approach to tendinopathy and load management was completely different. His explanation made so much sense, and within weeks my pain decreased significantly. I finally feel strong, supported, and back in control!” Amy S
3. How We Assess Your Hip
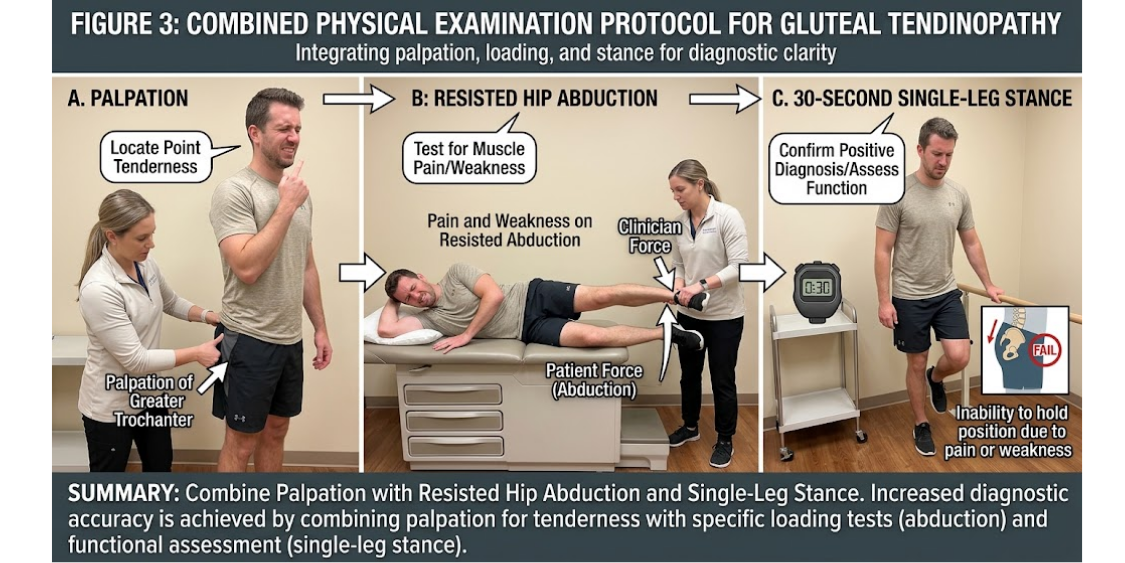
We review your symptoms, activity history, and movement patterns, then use a combination of clinical tests to assess your hip.
- Palpation: Checking whether pressure over the outside of your hip reproduces your familiar pain.
- Single-leg stance: Assessing your symptoms and tolerance while standing on one leg.
- Movement and strength tests: Evaluating hip movement, resisted strength, and response to loading.
A 2024 systematic review by Kinsella and colleagues found that combining greater trochanteric palpation with resisted hip abduction can improve diagnostic accuracy for GTPS. No single test reliably confirms the diagnosis in every patient.
Do you need an MRI? Usually, not as a first step. Many cases can be assessed clinically. Imaging may be appropriate if the diagnosis is uncertain, a significant tendon tear is suspected, or symptoms are not improving as expected.
Research: Kinsella et al. (2024).
 4. Why Does It Happen?
Several factors may contribute to gluteal tendinopathy.
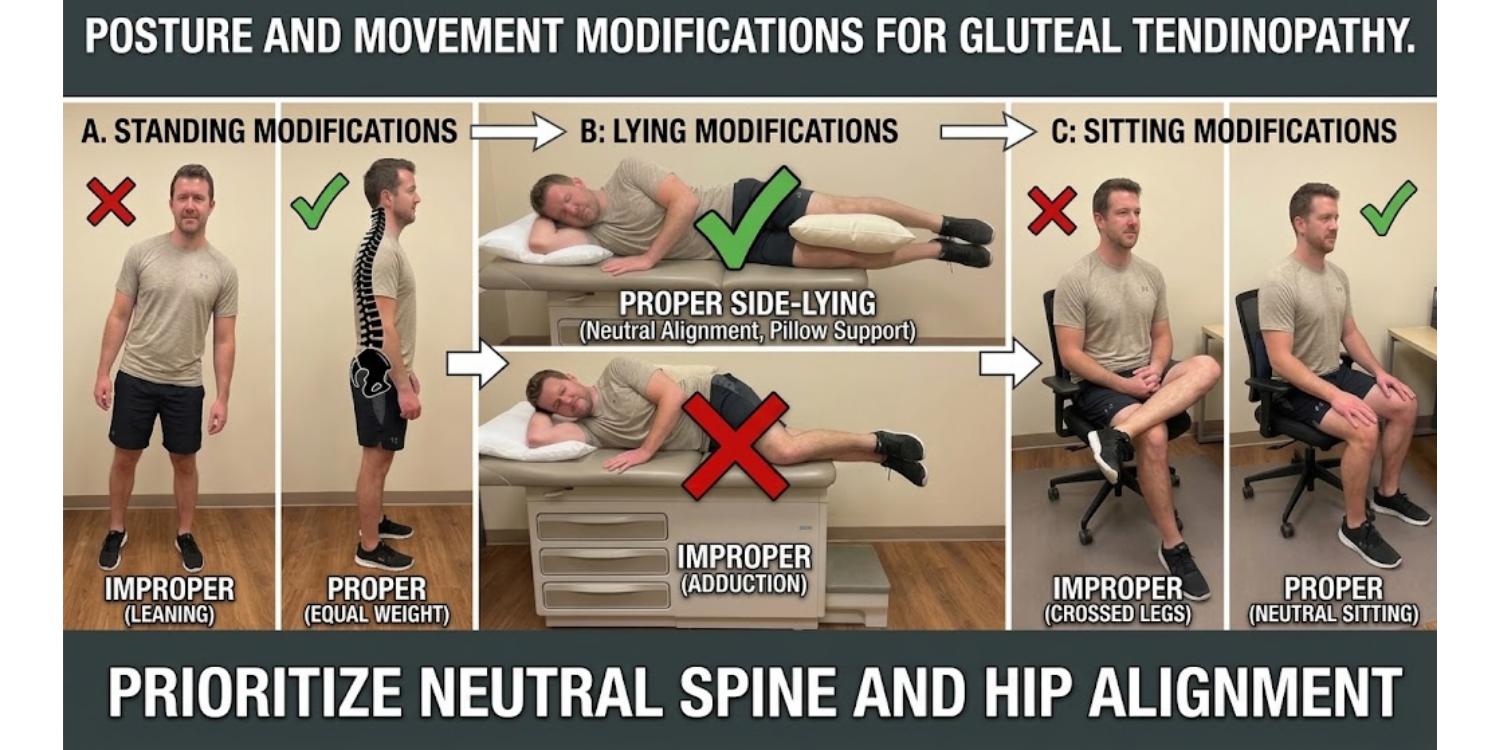
- Tendon compression: Crossing your legs, leaning heavily onto one hip, or allowing your upper leg to fall inward during side-sleeping can increase compression around the tendons.
- Changes in activity: A sudden increase in walking distance, running mileage, hills, or gym training may exceed your current capacity.
- Hormonal factors: Changes in oestrogen during perimenopause and menopause may influence connective tissue health and tendon function, potentially contributing to gluteal tendinopathy in some women. However, low oestrogen is not a proven direct cause. A 2022 randomized controlled trial by McMillan and colleagues investigated menopausal hormone therapy and exercise in postmenopausal women with greater trochanteric pain syndrome. The findings did not establish hormone therapy as a routine treatment for this condition. Education, load management, and progressive strengthening remain central to rehabilitation. If you have concerns about hormonal changes, discuss them with your healthcare professional.
Understanding your contributing factors helps us tailor your treatment.
Research: McMillan et al. (2022).
5. Evidence-Based Treatment & Recovery
Research supports education, appropriate load management, and progressive strengthening as key components of rehabilitation.
In the landmark LEAP trial, Mellor and colleagues (2018) found that education plus exercise produced better overall improvement than corticosteroid injection or a wait-and-see approach at eight weeks. At 52 weeks, overall improvement remained better than with injection, although pain intensity did not differ significantly between those two groups.
Two systematic reviews published in 2024 by Cordeiro and colleagues and Kjeldsen and colleagues provide additional support for exercise-based rehabilitation, while noting limitations in the available evidence.
Step 1: Load Management & Practical Adjustments
We help you modify activities and positions that consistently aggravate your symptoms.
- Avoid prolonged standing while leaning heavily onto one hip.
- Reduce leg crossing if it increases your pain.
- Try sleeping with a pillow between your knees, if comfortable.
- Adjust walking distance, running volume, hills, or gym training according to your symptoms.
- Maintain comfortable movement rather than stopping all activity unnecessarily.
 Step 2: Progressive Strengthening
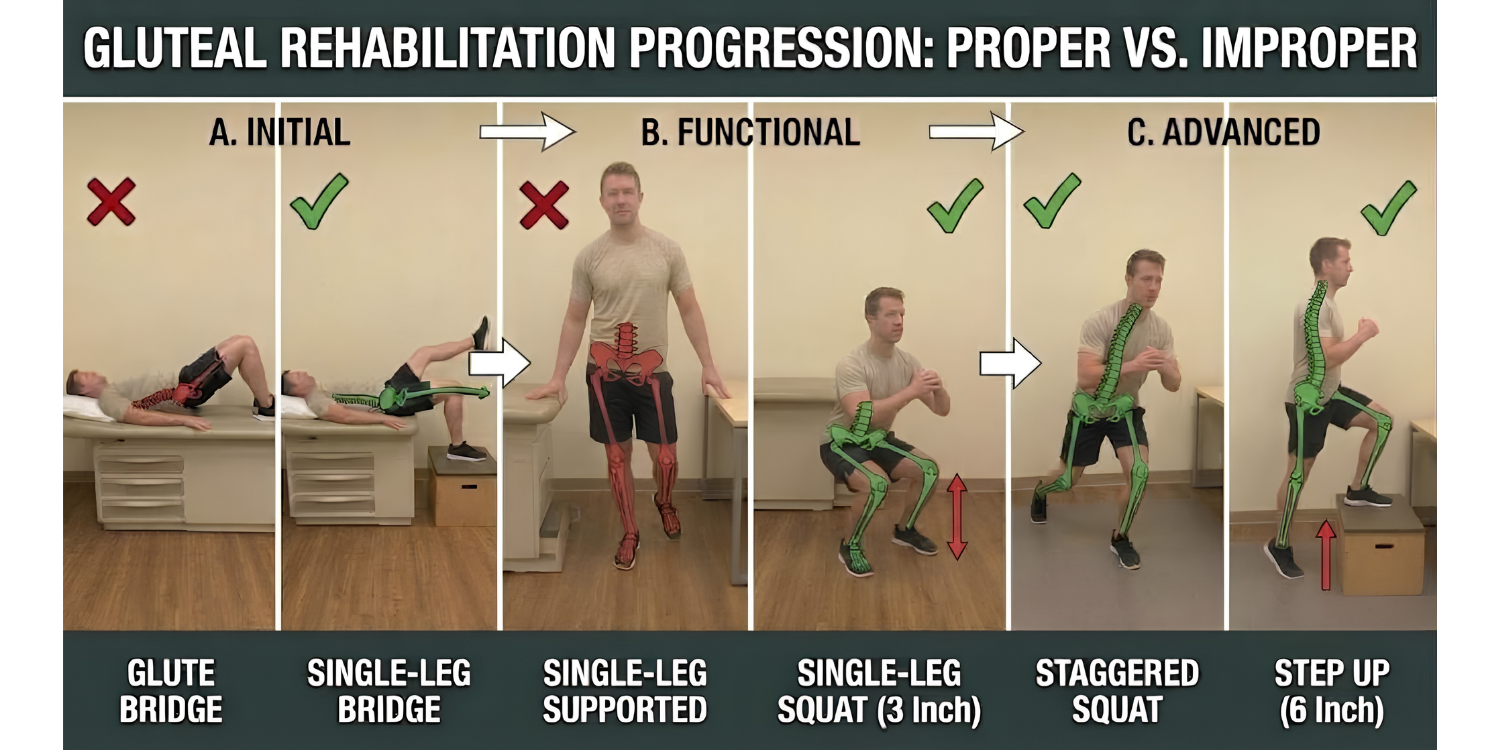
We gradually build your hip’s capacity through exercises tailored to your needs, which may include:
- Isometric exercises to introduce controlled muscle loading.
- Bridges and hip abduction exercises to build strength.
- Squats and step-ups to improve functional capacity.
- Progressive single-leg exercises to prepare for running and sport.
Your program is adjusted according to your strength, symptoms, goals, and response to loading.
Rest, injections, and other treatments may have a role in selected cases, but they should be considered within an individualized plan rather than as universal solutions.
Research: Mellor et al. (2018); Cordeiro et al. (2024); Kjeldsen et al. (2024).
 6. How to Gauge Progress: The Stoplight Rule
These pain ranges are general guidance, not universal clinical thresholds.
- Green — mild discomfort (around 0–2/10): You may be able to continue if your movement remains controlled and symptoms settle.
- Amber — moderate discomfort (around 3–4/10): Consider reducing resistance, repetitions, range of motion, or total activity.
- Red — substantial or worsening pain (around 5+/10): Stop or substantially modify the activity, particularly if pain is sharp, escalating, or changing how you move.
Everyone responds differently to exercise. These pain levels are general guidelines, not strict rules. Adjust your activity based on your symptoms and how you feel later that day and the following morning.
Check Your 24-Hour Response
Notice how your hip feels later that day and the following morning. If pain, sleep, walking, or daily activities are noticeably worse than usual, reduce the next session’s load or seek guidance.
Your symptoms do not have to disappear completely after every session. The goal is gradual improvement in function and load tolerance without repeated, significant flare-ups.
7. Measuring Rehabilitation Progress
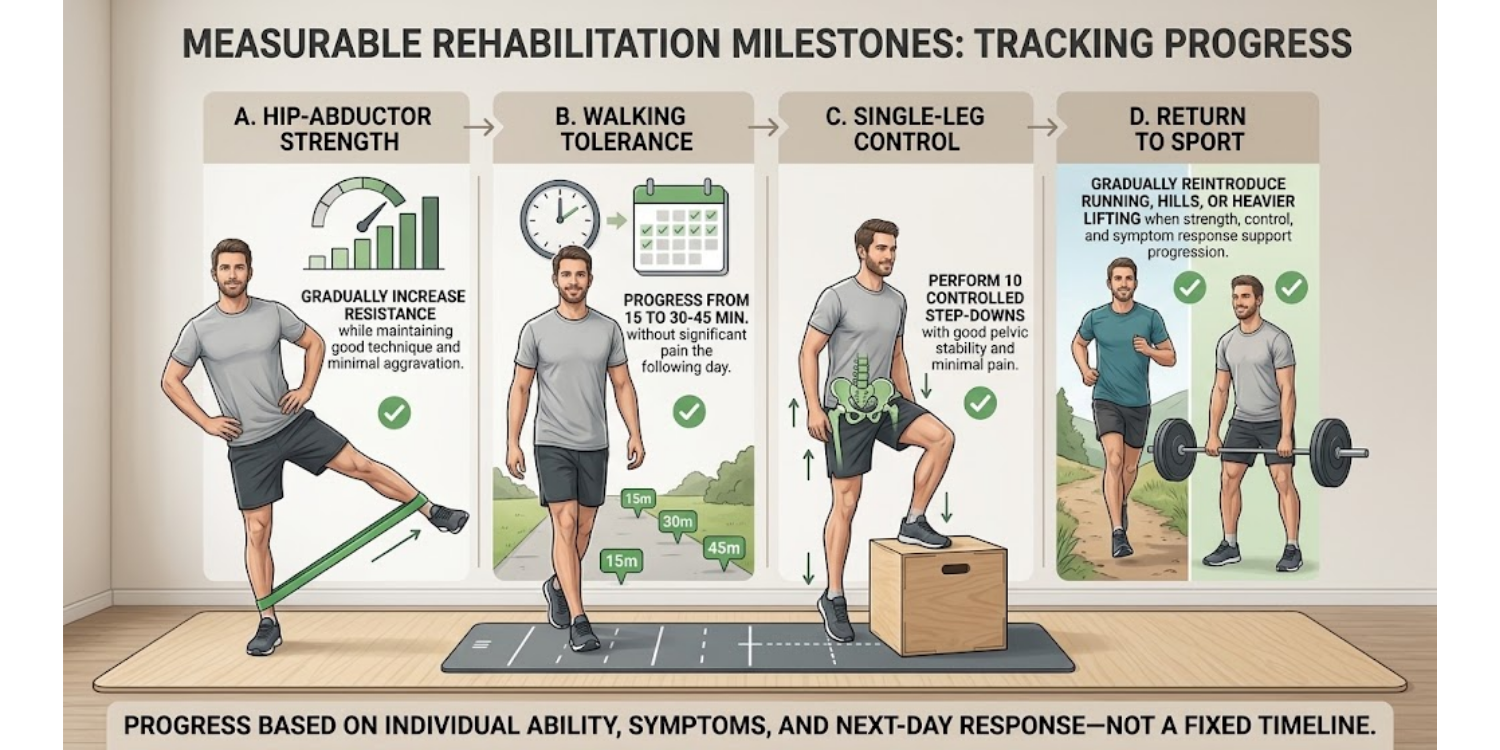
Recovery looks different for everyone. We track your progress by looking at how comfortably you move and how well your hip handles everyday activities and exercise.
We may monitor:
- Hip strength: Gradually building strength with controlled movements.
- Walking tolerance: Increasing walking distance as symptoms allow.
- Balance and control: Improving stability during single-leg activities.
- Return to sport: Gradually increasing running, training, and sport-specific activities.
Your progress depends on your goals, symptoms, and how your hip responds to exercise. We’ll adjust your program as your strength and confidence improve.
A practical guide to relieving outer hip pain and recovering from gluteal tendinopathy.
 Frequently Asked Questions
Do I need to stop running or working out?
Not necessarily. We can modify your training volume, intensity, frequency, or specific exercises while gradually rebuilding your hip’s capacity.
Is this hip bursitis?
Not necessarily. Gluteal tendinopathy affects the gluteal tendons, while GTPS can also involve nearby bursae and other tissues. An assessment helps distinguish the possible contributors.
How long does it take to improve?
Recovery varies depending on symptom duration, activity demands, and current load tolerance. We establish realistic goals and progress your rehabilitation according to your response rather than promising a fixed recovery date.
Can I sleep on my side?
Often, yes, if you find a comfortable position. If lying on the affected hip hurts, try sleeping on the opposite side with a pillow between your knees, or on your back with pillows supporting your legs.
Ready to Get Back to Doing What You Love?
Stop guessing. Start rebuilding.
You don’t have to navigate persistent hip pain on your own.
At Performance Sport & Spine, we’ll help you understand the factors contributing to your symptoms and develop a clear, progressive plan tailored to your goals.
Whether you want to return to running, hiking, lifting, sport, or simply moving comfortably throughout your day, we’re here to help you move forward.
Performance Sport & Spine
Call us: (425) 896-7151
References
- Mellor R, Bennell K, Grimaldi A, et al. Education plus exercise versus corticosteroid injection use versus a wait and see approach on global outcome and pain from gluteal tendinopathy: prospective, single blinded, randomised clinical trial. BMJ. 2018;361:k1662. https://doi.org/10.1136/bmj.k1662
- Kinsella R, Semciw AI, Hawke LJ, Stoney J, Choong PFM, Dowsey MM. Diagnostic accuracy of clinical tests for assessing greater trochanteric pain syndrome: a systematic review with meta-analysis. Journal of Orthopaedic & Sports Physical Therapy. 2024;54(1):26–49. https://doi.org/10.2519/jospt.2023.11890
- Cordeiro TTP, Rocha EAB, Scattone Silva R. Effects of exercise-based interventions on gluteal tendinopathy: systematic review with meta-analysis. Scientific Reports. 2024;14:3343. https://doi.org/10.1038/s41598-024-53283-x
- Kjeldsen T, Hvidt KJ, Bohn MB, Mygind-Klavsen B, Lind M, Semciw AI, Mechlenburg I. Exercise compared to a control condition or other conservative treatment options in patients with greater trochanteric pain syndrome: a systematic review and meta-analysis of randomized controlled trials. Physiotherapy. 2024;123:69–80. https://doi.org/10.1016/j.physio.2024.01.001
- McMillan RM, Ganderton CL, Cook JL, et al. Does menopausal hormone therapy, exercise, or both improve pain and function in postmenopausal women with greater trochanteric pain syndrome? A 2 × 2 factorial randomized clinical trial. The American Journal of Sports Medicine. 2022;50(2):515–525. https://doi.org/10.1177/03635465211061142
Educational disclaimer: This article is for educational purposes only and does not replace individualized medical advice, diagnosis, or treatment. Seek appropriate assessment for severe, worsening, or unexplained symptoms.


