

By Dr. Zach Greenwade, DC, MS | Published: August 19th, 2026
Not all knee pain is the same. Where you hurt, what aggravates the pain, how the knee responds afterward, and whether you have swelling or mechanical symptoms can provide important clues about what may be contributing to your symptoms.
This guide covers five common causes of knee pain. It is designed to help you recognize patterns, not to provide a definitive diagnosis. Several knee conditions can produce similar symptoms, and a clinical evaluation may be necessary to determine the actual cause.
📹 Watch the Full Video Guide
Follow along with Dr. Zach as he demonstrates knee anatomy, discusses common clinical findings, and explains how different knee conditions can present.
Watch on YouTube: 5 Most Common Causes of Knee Pain (How to Tell Them Apart)

Where Does Your Knee Hurt?
🔴 Around/behind the kneecap → Patellofemoral pain
🔴 Above or below the kneecap → Quadriceps/patellar tendinopathy
🔴 Along the joint line → Meniscal problem
🔴 Deep knee pain + stiffness → Osteoarthritis
🔴 Outside of the knee with running/cycling → ITB-related pain
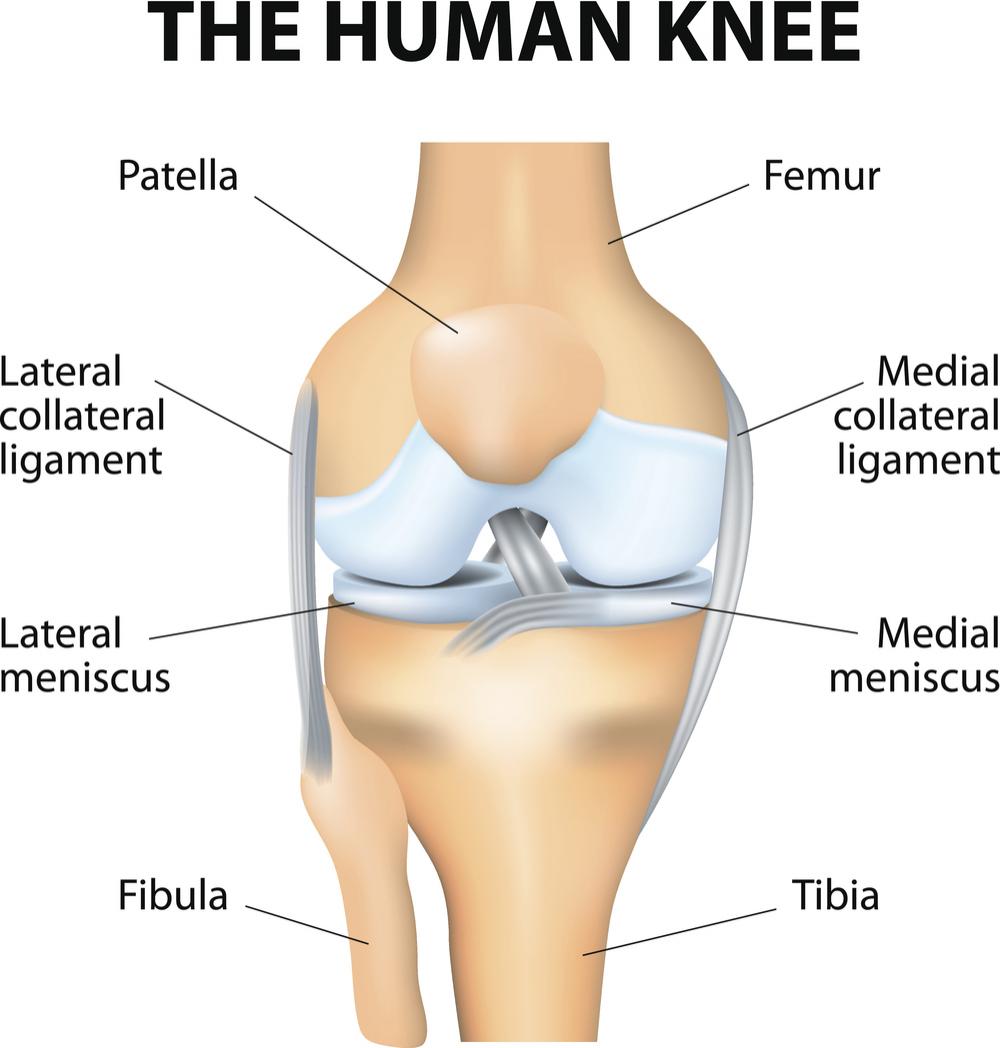
Basic Knee Anatomy
The knee is a complex joint made up of bones, cartilage, tendons, ligaments, muscles, and other soft tissues.
- Femur: The thigh bone.
- Tibia: The main weight-bearing bone of the lower leg.
- Fibula: The smaller bone on the outside of the lower leg.
- Patella: The kneecap, which helps the quadriceps generate force.
- Menisci: C-shaped pieces of fibrocartilage between the femur and tibia that help distribute load and improve joint stability.
- Tendons: Connect muscles to bones, including the quadriceps and patellar tendons.
- Ligaments: Help stabilize the knee by connecting bone to bone.
 The 5 Common Causes of Knee Pain
1. Knee Osteoarthritis
What it is
Knee osteoarthritis (OA) is a condition involving changes to the entire joint, including cartilage, bone, synovium, and other surrounding tissues. It is not simply “wearing away” of cartilage.
Typical pain pattern
Pain is often felt deep within the knee and may be more noticeable on the inside, outside, or around the kneecap depending on which parts of the joint are affected.

Common symptoms
- Pain that increases with walking, stairs, squatting, or prolonged activity
- Stiffness after periods of inactivity
- Morning stiffness, typically relatively brief
- Swelling or a feeling of fullness in the knee
- Reduced ability to fully bend or straighten the knee
- Crepitus or grinding sensations
Symptoms can vary considerably from person to person.
How is it evaluated?
A clinician considers the history and physical examination and may use X-rays when appropriate. Importantly, the amount of arthritis seen on an X-ray does not always correspond to the amount of pain someone experiences.
Key takeaway: OA is more likely when knee pain is accompanied by activity-related symptoms, stiffness, reduced motion, and other clinical findings consistent with joint degeneration.
2. Patellofemoral Pain
Sometimes called “runner’s knee,” patellofemoral pain refers to pain arising from the tissues around and behind the kneecap.
Typical pain pattern
Pain is generally felt:
- Around the kneecap
- Behind the kneecap
- Underneath the kneecap
It can be difficult to pinpoint to one exact spot.
 Common triggers
Pain often increases when the knee is repeatedly loaded while bent, such as during:
- Squatting
- Lunging
- Running
- Going downstairs
- Getting up from a chair
- Prolonged sitting with the knee bent
A sudden increase in running, exercise volume, or other activity can contribute.
What about kneecap tracking?
You may hear about the J-sign or other tests intended to evaluate patellar tracking.
These observations can provide information about knee mechanics, but they do not diagnose patellofemoral pain by themselves. Patellofemoral pain is generally considered a multifactorial, load-related condition rather than simply a kneecap that is “out of alignment.”
How is it evaluated?
Diagnosis is generally based on the overall pattern of symptoms and physical examination, particularly whether the person’s familiar pain can be reproduced with activities that load the patellofemoral joint.
Key takeaway: Pain around the kneecap that increases with squatting, stairs, running, or prolonged sitting is a common pattern of patellofemoral pain.
3. Meniscus Problems
The menisci are important pieces of fibrocartilage between the femur and tibia. They can be injured acutely or develop degenerative changes over time.
 Typical pain pattern
Pain is often localized around the inside or outside joint line, although symptoms can vary.
Common triggers
Symptoms may increase with:
- Twisting or pivoting
- Deep squatting
- Kneeling
- Getting in and out of a car
- Certain loaded positions
Other symptoms
Some people experience:
- Clicking
- Catching
- Swelling
- A sensation of instability
- Difficulty fully bending or straightening the knee
True mechanical locking, where the knee becomes physically stuck and cannot move through its normal range, is more concerning and deserves clinical evaluation.
What about the Thessaly or McMurray tests?
Tests such as the Thessaly and McMurray tests, along with joint-line tenderness, may provide useful information during a clinical examination.
However, no single test can reliably confirm or rule out a meniscal tear.
MRI can identify meniscal abnormalities, but an important distinction is that seeing a tear on MRI does not necessarily mean the tear is the source of the person’s pain. Degenerative meniscal changes are relatively common, particularly with increasing age.
Key takeaway: Joint-line pain associated with twisting, squatting, swelling, or mechanical symptoms can raise suspicion for meniscal involvement, but the overall clinical picture matters.
4. Patellar or Quadriceps Tendinopathy
Tendinopathy involves changes in a tendon associated with repetitive loading and insufficient recovery. It isn’t simply an inflammatory condition.
Patellar tendinopathy affects the tendon below the kneecap; quadriceps tendinopathy affects the tendon above it.
 Typical pain pattern
Unlike the more diffuse discomfort of some knee conditions, tendon pain is often relatively localized, and people can frequently identify the painful area with one or two fingers.
The three useful clues
1. Load dependence
Tendon pain generally changes according to the amount and type of load placed on the tendon.
For example, jumping or heavy squatting may provoke more symptoms than walking.
2. Warm-up response
Some people notice that tendon pain decreases as they warm up and begin moving.
However, feeling better during exercise does not necessarily mean the tendon is healthy or that continuing to increase the load is appropriate.
3. Response over the following 24 hours
Perhaps one of the most useful concepts in managing tendinopathy is the tendon’s response to loading afterward.
You may feel relatively good during exercise but experience increased pain or stiffness later that day or the following morning.
This delayed response can help determine whether the current exercise load is appropriate.
How is it evaluated?
A clinician may assess:
- Localized tendon tenderness
- Pain during resisted knee extension
- Squatting or jumping ability
- Strength
- The tendon’s response to different loads
Key takeaway: Localized pain in or around the patellar/quadriceps tendon that responds predictably to loading is consistent with tendinopathy, but the diagnosis should be based on the overall clinical picture.
5. Iliotibial Band-Related Lateral Knee Pain
Iliotibial band (ITB)-related pain is a common cause of activity-related pain on the outside of the knee, particularly in runners and cyclists.
 Typical pain pattern
Pain is usually localized to the outer/lateral aspect of the knee.
It may feel sharp or burning during repetitive activity.
Common triggers
Symptoms may occur during activities involving repeated knee flexion and extension, particularly:
- Running
- Downhill running
- Cycling
- Hiking
Historically, IT band syndrome has often been described as the IT band repeatedly “rubbing” over the bone.
Current thinking emphasizes compression and loading of the tissues around the lateral femoral epicondyle, rather than simply an IT band that is “too tight.”
What about foam rolling?
Aggressively foam rolling directly over the IT band is unlikely to “loosen” the band in the way it is often claimed to. The IT band is dense connective tissue and isn’t meaningfully lengthened by simply rolling over it.
That doesn’t mean foam rolling other surrounding muscles can never feel helpful—it simply shouldn’t be presented as a way to mechanically “break up” or lengthen the IT band itself.
How is it evaluated?
A clinician may look at:
- The location of tenderness
- The activity that reproduces symptoms
- Hip and leg strength
- Running/cycling mechanics
- Training volume and recent changes in activity
Tests such as the Noble compression test can be used as part of an examination, but they should not be interpreted in isolation as proof of IT band syndrome.
Key takeaway: Localized lateral knee pain that develops predictably during repetitive activity is consistent with ITB-related pain, particularly when other causes of lateral knee pain have been considered.
Comparing Common Knee Pain Patterns
| Condition | Typical location | Common aggravating activities | Useful clues |
|---|---|---|---|
| Knee OA | Deep knee; may be medial, lateral, or around kneecap | Walking, stairs, prolonged activity | Stiffness, swelling, reduced motion, age/risk factors, imaging when appropriate |
| Patellofemoral pain | Around/behind kneecap | Squatting, stairs, running, prolonged sitting | Pain with loaded knee flexion; often diffuse around patella |
| Meniscal problem | Along inside or outside joint line | Twisting, pivoting, deep squatting | Joint-line pain, swelling, catching/locking in some cases |
| Patellar/quadriceps tendinopathy | Localized below/above kneecap | Jumping, running, squatting, resisted extension | Load-dependent pain, possible warm-up response, next-day response |
| ITB-related pain | Outside of knee | Running, cycling, downhill activity | Localized lateral pain associated with repetitive activity |
One Important Point: Knee Pain Doesn’t Always Fit Into One Box
These five conditions are common, but they don’t represent every cause of knee pain.
Other possibilities include:
- Ligament injuries
- Bursitis
- Baker’s cyst
- Hip-related or referred pain
- Lumbar nerve-related pain
- Inflammatory arthritis
- Stress injuries
- Other tendon disorders
- Less common joint or bone conditions
And sometimes more than one problem exists at the same time.
For example, someone can have knee osteoarthritis and patellar tendon pain, or patellofemoral pain and an irritated meniscus.
When Should You Get Your Knee Evaluated?
Consider professional evaluation if you have:
- Significant swelling after an injury
- Inability to bear weight
- A knee that is truly locked
- Repeated giving way
- Significant loss of motion
- Persistent pain that isn’t improving
- Pain following significant trauma
- Fever, redness, or unusual warmth around the joint
- Symptoms that are progressively worsening
The Bottom Line
The location and behavior of your pain provide clues, but no single home test can reliably tell you exactly what is wrong with your knee.
A better approach is to consider the entire pattern:
Where does it hurt? → What loads it? → What makes it better or worse? → How does it respond afterward? → Are there swelling or mechanical symptoms?
Those clues, combined with an appropriate physical examination when needed, are much more useful than relying on one positive self-test.
Identifying the likely pain pattern is only the first step. The next step is determining what loads your knee can tolerate and gradually restoring its strength and function.
About the Author
Dr. Greenwade, DC, MS is an evidence-based sports chiropractor, movement specialist, and the founder of Performance Sport & Spine, serving patients across the Eastside in Redmond and Seattle. Holding a Master of Science in sports medicine alongside a Doctorate of Chiropractic, Dr. Greenwade specializes in modern physical medicine, progressive loading, and active, movement-based recovery. The clinic’s mission is to help active individuals and office professionals resolve acute and chronic musculoskeletal conditions without unnecessary injections, medications, or surgeries.
Medical Disclaimer: The information provided in this article, including text, graphics, images, and other material, is for educational and informational purposes only. It is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of a qualified healthcare provider with any questions you may have regarding a medical condition or treatment plan.


